

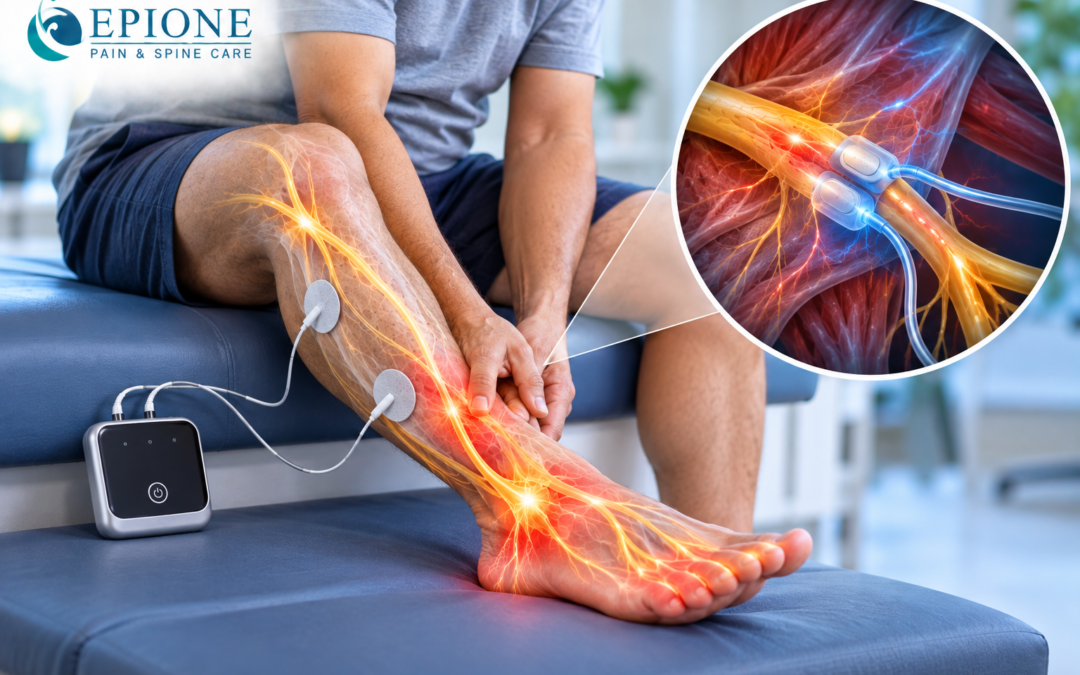
Quick answer: Peripheral nerve stimulation (PNS) delivers electrical stimulation near a selected peripheral nerve to modulate pain signaling. It is being studied and used in selected neuropathic pain conditions, but candidacy depends on a clear pain target, prior treatment, device availability and specialist assessment.
Key takeaways
- Peripheral nerve stimulation for neuropathy should be understood in clinical context, not from one symptom or scan alone.
- The most useful treatment plan starts with a plausible pain mechanism and measurable functional goals.
- Newer research can improve patient selection, but emerging evidence should not be marketed as a guaranteed cure.
People rarely search for “peripheral nerve stimulation for neuropathy” because they want a textbook definition. Usually there is a real decision behind the search: a scan report that is confusing, pain that has not improved, or a new treatment name that sounds promising but is hard to evaluate. This guide is written to make that decision easier. It explains what clinicians mean by the term, where the evidence is strong or still emerging, and which questions are worth taking to a specialist appointment.
What PNS actually targets
Peripheral nerve stimulation is different from spinal cord stimulation because the electrode is placed near a peripheral nerve rather than in the epidural space near the spinal cord. That makes PNS conceptually attractive when pain can be traced to a specific peripheral nerve or nerve territory.
The technology includes temporary and implantable systems depending on indication and region. It should not be confused with TENS, which applies electrodes to the skin. PNS is an interventional neuromodulation technique and requires careful patient selection.
Why neuropathy is a challenging target
Neuropathy can be focal, as after a particular nerve injury, or diffuse, as in diabetic polyneuropathy. A treatment aimed at one peripheral nerve may be logical for focal pain but less suitable when symptoms involve both feet in a broad stocking distribution. This is why diagnosis comes before device choice.
A 2026 narrative review examined spinal cord stimulation, DRG stimulation and PNS for painful diabetic neuropathy. The field is evolving, and the strength of evidence differs across technologies. Patients should be told which parts of a treatment plan are established, which are emerging and which remain investigational for a particular condition.
What happens before stimulation is considered
A neuropathic pain treatment plan usually reviews the underlying disease, medication options, foot or limb protection, rehabilitation, sleep and function. In diabetes, glucose management remains central because neuromodulation does not replace metabolic care.
When pain is focal, a targeted examination and sometimes nerve block injections can help define the pain generator. If symptoms remain disabling despite appropriate care, a specialist may discuss neuromodulation, including PNS or spinal cord stimulation, depending on the pattern and available evidence.
Potential advantages and limitations
Because PNS targets a peripheral nerve, it may avoid some of the anatomical demands of epidural lead placement. In some situations, temporary systems allow treatment without a permanent implant. However, not every painful nerve is easy or safe to stimulate, and diffuse neuropathy may require a different strategy.
Possible complications include infection, lead movement, skin irritation, unwanted stimulation, device malfunction and inadequate pain relief. Some systems have additional restrictions related to imaging or activity. These details vary by device and should be discussed specifically rather than generalized.
What meaningful success should look like
Pain reduction is important, but function matters just as much. A good outcome might mean walking farther, sleeping better, tolerating shoes, returning to work or reducing rescue medication. Setting those goals before a trial or procedure makes the decision more grounded.
Neuromodulation also requires follow-up. Programming, device checks and rehabilitation may be part of the longer-term plan. A pain management center considering PNS should be able to explain who manages the device after placement and what happens if symptoms change.
A cautious view of emerging evidence
Interest in PNS is growing, but a 2026 review does not mean every neuropathy patient should receive stimulation. Study populations, devices and outcomes vary. The most defensible use of new evidence is to refine patient selection and shared decision-making, not to turn promising research into a blanket promise.
People with rapidly progressive weakness, infected skin near a potential implant site, severe uncontrolled systemic illness or unclear diagnosis need broader evaluation before any device discussion. The first question is still “What is causing the pain?” not “Which device can be implanted?”
What current evidence can—and cannot—tell us
A useful way to read newer pain research is to separate three questions: does the mechanism make biological sense, has it been demonstrated in the type of patient being discussed, and does treating that mechanism improve outcomes that matter to patients? For peripheral nerve stimulation for neuropathy, those questions are more useful than asking whether the topic is simply “new” or “advanced.” Related search terms such as PNS for nerve pain, diabetic neuropathy neuromodulation, peripheral nerve stimulator, refractory neuropathy treatment describe overlapping interests, but they should not be treated as interchangeable diagnoses. A study may show promising average improvement while still leaving uncertainty about which individual will respond, how long benefit lasts, and whether the result compares favorably with simpler care. This is particularly important in pain medicine because many studies enroll highly selected patients, use different definitions of success, and combine pain scores with functional outcomes in different ways. For patients, the safest interpretation is that evidence can guide a conversation; it cannot guarantee a personal result. For patients, the same principle improves decision-making: understand what is known, what remains uncertain, and whether the evidence is observational, randomized, or mainly mechanistic.
How a specialist turns the information into a treatment plan
When a patient is trying to understand peripheral nerve stimulation for neuropathy, the next step should not be chosen from the search result alone. A specialist first asks what problem needs to be solved: Is the priority walking, sleeping, returning to work, reducing medication, or understanding a confusing scan? The clinician then builds a differential diagnosis, checks for warning signs, reviews previous care and decides whether more testing would actually change management. Where appropriate, that assessment can connect to neuropathic pain treatment or nerve block injections depending on which diagnosis best matches the symptoms. The purpose is to move from a broad symptom or question to the most relevant condition or treatment pathway, without assuming that every patient needs the same test or procedure.
A practical symptom diary before your consultation
Before a consultation, track symptoms for one to two weeks if the condition is stable and non-urgent. Note where the pain begins, where it spreads, what time of day it is worst, which movements or positions change it, whether there is numbness or weakness, how sleep is affected, and what you can no longer do comfortably. Record medicines and supplements, previous injections or procedures, and the actual benefit rather than only whether they were “tried.” If you have imaging, bring both the report and the images when possible. This kind of preparation creates a more human and more accurate consultation because the discussion starts with your lived pattern of symptoms instead of a generic label. It also gives the clinician a baseline for measuring whether treatment is genuinely helping. If symptoms are rapidly worsening, accompanied by new neurological deficits, fever, major trauma, loss of bladder or bowel control, or another emergency feature, do not wait to complete a diary—seek prompt medical assessment.
Expert pain assessment in Hyderabad
For patients in Hyderabad who are exploring newer pain technologies or medicines, expert interpretation matters as much as the headline. Epione identifies Dr. Minal Chandra, MBBS, DA, DNB, FIPM, as its Co-Founder and Consultant Pain Specialist with 15+ years of experience in interventional pain medicine. A consultation can help place peripheral nerve stimulation for neuropathy in the context of your diagnosis, previous treatment and options that are actually available locally. Because regulatory approval, device availability and evidence can differ by country and condition, an emerging treatment should not be presented as automatically suitable or available.
Learn more about Epione’s pain specialists and multidisciplinary care: Dr. Minal Chandra at Epione | Book an appointment
References
- 2026 review of neuromodulation therapies for diabetic neuropathy
- 2026 meta-analysis of SCS for painful diabetic neuropathy
If pain is limiting sleep, work, walking or daily activity, consider a specialist review rather than choosing a procedure from a scan or search result alone. Request an Epione consultation and ask about Dr. Minal Chandra’s availability.
Frequently Asked Questions
1. What is peripheral nerve stimulation?
Peripheral Nerve Stimulation is an interventional pain treatment described in this article. Its role depends on the pain diagnosis, target and available evidence. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
2. What is the main purpose of peripheral nerve stimulation?
Modulate pain signals from a selected peripheral nerve. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
3. How is peripheral nerve stimulation different from spinal cord stimulation and non-invasive TENS?
The procedures target different parts of the pain pathway or use different technology. The choice should reflect the patient’s diagnosis and pain distribution. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
4. Who may be considered for this procedure?
A clear pain target, specialist assessment and review of prior treatments. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
5. Is it a first-line treatment?
Usually not. Most interventional or implantable procedures are considered after appropriate conservative and diagnosis-specific care. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
6. Does everyone need a trial first?
Some neuromodulation procedures use a temporary trial, while other procedures do not. The protocol depends on the device, indication and center. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
7. Will it cure the underlying disease?
Usually not. Most pain procedures aim to reduce pain signaling or improve function; they do not necessarily reverse the disease causing the pain. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
8. How much pain relief should I expect?
Response varies. Published averages cannot predict an individual outcome, so realistic goals should include function as well as pain reduction. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
9. How long can benefit last?
Duration depends on the procedure, diagnosis, device or nerve target and individual response. Some treatments are temporary, while implants require long-term follow-up. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
10. What are the main risks?
Infection, lead movement, device problems, unwanted stimulation and inadequate relief. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
11. Can the procedure be repeated?
Sometimes, depending on the treatment and reason symptoms returned. Repeating a procedure should follow reassessment rather than happen automatically. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
12. Do I need to stop blood thinners?
Some procedures require modification of anticoagulant or antiplatelet therapy, but changes must be coordinated with the prescribing clinician. Never stop these medicines on your own. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
13. Is the procedure painful?
Local anesthesia and other comfort measures are commonly used, but the experience depends on the procedure. Ask the treating team what to expect. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
14. How soon can I return to normal activity?
Recovery instructions vary. Many minimally invasive procedures allow early activity, while implanted devices require more restrictions during healing. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
15. Can I have an MRI afterward?
MRI compatibility depends on the specific device and system. Patients with implants should always provide device details before any MRI. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
16. Does age prevent treatment?
Not by itself. Medical fitness, diagnosis, infection risk, medications and functional goals are more important than age alone. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
17. Can physiotherapy continue after the procedure?
Often yes, and rehabilitation may be important to convert pain relief into better function. Timing should follow the treating clinician’s advice. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
18. When should I call the doctor after a procedure?
Contact the treating team for fever, increasing redness or drainage, new neurological symptoms, severe unexpected pain, or any post-procedure concern listed in your discharge instructions. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
19. How do I know whether a center has the right expertise?
Ask how often the team performs the procedure, how patients are selected, how outcomes are tracked, and who provides long-term follow-up. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
20. What is the most important question before proceeding?
Ask exactly what pain generator is being targeted and what evidence suggests that treating it is likely to improve your function. For peripheral nerve stimulation for neuropathy, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.