

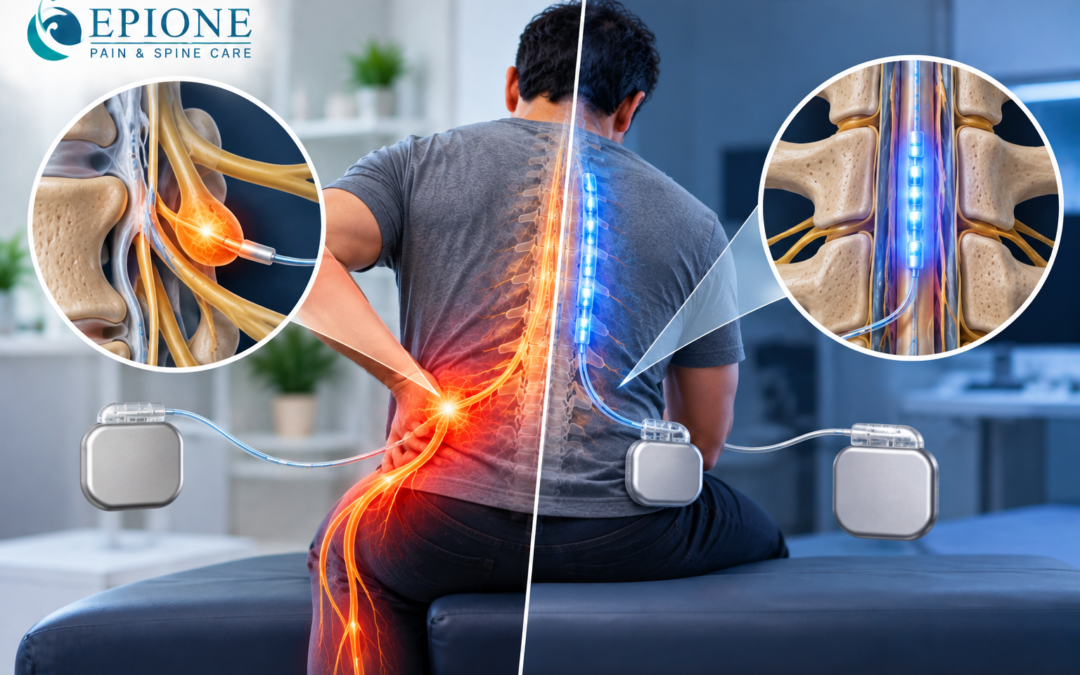
Quick answer: Dorsal root ganglion (DRG) stimulation and spinal cord stimulation (SCS) both use implanted electrical neuromodulation, but they target different neural structures. DRG stimulation can provide highly focal coverage for selected neuropathic pain regions, while SCS is often used for broader trunk or limb pain patterns.
Key takeaways
- Drg stimulation vs spinal cord stimulation should be understood in clinical context, not from one symptom or scan alone.
- The most useful treatment plan starts with a plausible pain mechanism and measurable functional goals.
- Newer research can improve patient selection, but emerging evidence should not be marketed as a guaranteed cure.
People rarely search for “DRG stimulation vs spinal cord stimulation” because they want a textbook definition. Usually there is a real decision behind the search: a scan report that is confusing, pain that has not improved, or a new treatment name that sounds promising but is hard to evaluate. This guide is written to make that decision easier. It explains what clinicians mean by the term, where the evidence is strong or still emerging, and which questions are worth taking to a specialist appointment.
Two forms of neuromodulation, different targets
Spinal cord stimulation places electrodes in the epidural space to modulate pain signaling at the spinal cord level. DRG stimulation places leads near the dorsal root ganglion, a sensory structure associated with a specific spinal level. That anatomical difference helps explain why DRG stimulation is often discussed for focal pain that is difficult to cover consistently with broader stimulation.
A 2026 review described DRG stimulation as an emerging targeted option for focal neuropathic syndromes. Another 2026 clinical review highlighted uses including complex regional pain syndrome, peripheral nerve injuries and selected groin or knee pain. These are specialized indications, not a general solution for all chronic pain.
Why pain location matters
Neuropathic pain can be diffuse or sharply localized. Someone with a small but intensely painful region after nerve injury has a different problem from someone with broad bilateral leg and back pain. DRG stimulation’s segmental targeting can be attractive when pain follows a specific sensory distribution.
In contrast, conventional spinal cord stimulation has a longer clinical history across several chronic back, leg and neuropathic pain conditions. The choice between systems depends on diagnosis, anatomy, prior treatment, regulatory availability and the experience of the treating team.
What assessment comes before an implant
A clinician should confirm that the pain is genuinely neuropathic or otherwise appropriate for neuromodulation, review imaging and neurological findings, evaluate psychosocial factors and determine whether less invasive care has been adequately tried. Neuropathic pain treatment may include medication, physical rehabilitation, nerve blocks and other options before implantable therapy is considered.
Targeted nerve block injections can sometimes help clarify a peripheral pain generator, although the role of blocks varies by diagnosis. The important point is that an implant should follow a diagnostic pathway, not replace one.
How trials and outcomes are judged
Many neuromodulation programs use a temporary trial to assess whether stimulation improves pain and function before permanent implantation. The definition of success should be individualized. A patient might value being able to wear a shoe, sit through work, sleep without repeated waking, or walk a certain distance more than a numeric pain score alone.
Long-term outcomes depend on patient selection, programming, device performance, follow-up and the underlying condition. Both DRG and SCS require ongoing care after implantation. Comparing the devices only by headline response rates can be misleading because studies often enroll different types of patients.
Risks and practical considerations
Both procedures involve implantation and therefore carry risks such as infection, bleeding, lead migration, hardware problems and failure to achieve adequate relief. DRG leads and SCS leads have different technical considerations, and revision rates depend on device, technique and experience. MRI compatibility and battery management should be discussed before surgery.
Availability also matters. Specific DRG systems may not be available in every region or center. A pain management center should explain which options are actually accessible and whether referral is appropriate rather than presenting emerging technology as a guaranteed in-house treatment.
The bottom line for patients
The best question is not “Which device is newer?” It is “Which neural target best matches my pain pattern, and is there enough evidence for my diagnosis?” For focal neuropathic pain, DRG stimulation may be discussed; for broader chronic back, leg or neuropathic pain, SCS may be considered. Some patients are candidates for neither.
A second opinion can be valuable when an implant is being considered. Bring prior imaging, operative reports, medication history and a list of treatments that genuinely helped or failed. That information makes the neuromodulation discussion much more specific.
What current evidence can—and cannot—tell us
A useful way to read newer pain research is to separate three questions: does the mechanism make biological sense, has it been demonstrated in the type of patient being discussed, and does treating that mechanism improve outcomes that matter to patients? For DRG stimulation vs spinal cord stimulation, those questions are more useful than asking whether the topic is simply “new” or “advanced.” Related search terms such as dorsal root ganglion stimulation, SCS for nerve pain, focal neuropathic pain treatment, neuromodulation for chronic pain describe overlapping interests, but they should not be treated as interchangeable diagnoses. A study may show promising average improvement while still leaving uncertainty about which individual will respond, how long benefit lasts, and whether the result compares favorably with simpler care. This is particularly important in pain medicine because many studies enroll highly selected patients, use different definitions of success, and combine pain scores with functional outcomes in different ways. For patients, the safest interpretation is that evidence can guide a conversation; it cannot guarantee a personal result. For patients, the same principle improves decision-making: understand what is known, what remains uncertain, and whether the evidence is observational, randomized, or mainly mechanistic.
How a specialist turns the information into a treatment plan
When a patient is trying to understand DRG stimulation vs spinal cord stimulation, the next step should not be chosen from the search result alone. A specialist first asks what problem needs to be solved: Is the priority walking, sleeping, returning to work, reducing medication, or understanding a confusing scan? The clinician then builds a differential diagnosis, checks for warning signs, reviews previous care and decides whether more testing would actually change management. Where appropriate, that assessment can connect to spinal cord stimulation or neuropathic pain treatment depending on which diagnosis best matches the symptoms. The purpose is to move from a broad symptom or question to the most relevant condition or treatment pathway, without assuming that every patient needs the same test or procedure.
A practical symptom diary before your consultation
Before a consultation, track symptoms for one to two weeks if the condition is stable and non-urgent. Note where the pain begins, where it spreads, what time of day it is worst, which movements or positions change it, whether there is numbness or weakness, how sleep is affected, and what you can no longer do comfortably. Record medicines and supplements, previous injections or procedures, and the actual benefit rather than only whether they were “tried.” If you have imaging, bring both the report and the images when possible. This kind of preparation creates a more human and more accurate consultation because the discussion starts with your lived pattern of symptoms instead of a generic label. It also gives the clinician a baseline for measuring whether treatment is genuinely helping. If symptoms are rapidly worsening, accompanied by new neurological deficits, fever, major trauma, loss of bladder or bowel control, or another emergency feature, do not wait to complete a diary—seek prompt medical assessment.
Expert pain assessment in Hyderabad
For patients in Hyderabad who are exploring newer pain technologies or medicines, expert interpretation matters as much as the headline. Epione identifies Dr. Minal Chandra, MBBS, DA, DNB, FIPM, as its Co-Founder and Consultant Pain Specialist with 15+ years of experience in interventional pain medicine. A consultation can help place DRG stimulation vs spinal cord stimulation in the context of your diagnosis, previous treatment and options that are actually available locally. Because regulatory approval, device availability and evidence can differ by country and condition, an emerging treatment should not be presented as automatically suitable or available.
Learn more about Epione’s pain specialists and multidisciplinary care: Dr. Minal Chandra at Epione | Book an appointment
References
- 2026 review of developments in dorsal root ganglion stimulation
- 2026 review of DRG stimulation evidence and clinical application
If pain is limiting sleep, work, walking or daily activity, consider a specialist review rather than choosing a procedure from a scan or search result alone. Request an Epione consultation and ask about Dr. Minal Chandra’s availability.
Frequently Asked Questions
1. What is the main difference between DRG stimulation and spinal cord stimulation?
Drg stimulation targets a dorsal root ganglion for more focal segmental coverage, while scs targets the spinal cord for broader neuromodulation. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
2. Can DRG stimulation and spinal cord stimulation occur together?
Yes. Pain mechanisms and diagnoses can overlap, which is why clinicians should avoid forcing every patient into a single category. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
3. Which one causes more severe pain?
Severity alone cannot reliably distinguish them. Either condition can be mild or disabling depending on the individual and the underlying mechanism. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
4. Can symptoms alone tell the difference?
Symptoms provide clues but are rarely enough by themselves. Distribution, triggers, examination findings and sometimes tests are needed. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
5. How are they diagnosed?
Assessment commonly involves specialist evaluation and, where appropriate, a temporary stimulation trial. The exact work-up depends on the presentation. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
6. Is MRI always needed?
No. Imaging is appropriate when it is likely to change management or investigate concerning features; it is not automatically required for every pain complaint. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
7. Can scan findings be misleading?
They can be overinterpreted. Structural abnormalities may be incidental, so imaging should be matched to the patient’s symptoms and examination. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
8. Do the treatments overlap?
Sometimes. Management may include neuromodulation after appropriate conservative and interventional care has been considered, but the emphasis changes according to the dominant mechanism. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
9. Can physiotherapy help both?
Often yes, although the goals and exercise selection may differ. Rehabilitation should be individualized rather than based only on a diagnosis label. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
10. Are injections used for both?
They may be used in selected situations, but the target, medication and purpose differ. A procedure is useful only when it matches a plausible pain generator. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
11. Which condition needs surgery more often?
That depends on structural severity, neurological compromise and response to non-surgical care. The name of the condition alone does not determine surgery. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
12. Can one condition be mistaken for the other?
Yes. Overlapping symptoms are common, which is why a focused examination and careful history matter. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
13. Can both become chronic?
Yes. Persistent symptoms can occur in either condition, especially when the underlying driver is not addressed or multiple pain mechanisms are active. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
14. Does pain location help?
Yes, location and radiation pattern can narrow the differential diagnosis, but location alone is not definitive. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
15. Are there warning signs that need urgent care?
New major weakness, bladder or bowel dysfunction, fever with severe pain, sudden severe headache, major trauma or other significant neurological symptoms require urgent assessment. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
16. How should treatment success be measured?
Use function as well as pain: walking, sleep, work, exercise tolerance and reduced flare frequency can be meaningful outcomes. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
17. Should I get a second opinion?
A second opinion can be useful when the diagnosis is uncertain, major surgery or an implant is proposed, or several treatments have failed. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
18. Can lifestyle changes help?
Sleep, graded activity, weight management where relevant, hydration and stress management can support treatment, but they should not be presented as substitutes for diagnosis. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
19. What should I ask my doctor?
Ask which diagnosis best explains your symptoms, what evidence supports it, what alternatives were considered and what result would make the plan change. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.
20. What is the safest way to choose between treatments?
Start with the diagnosis and least invasive effective option, then escalate only when expected benefit outweighs risk and there is a clear treatment target. For DRG stimulation vs spinal cord stimulation, the answer depends on the symptom pattern, examination findings, medical history and the goal of treatment. A qualified clinician can explain which findings are clinically important and whether testing, rehabilitation, medication or a targeted procedure is appropriate. Seek prompt medical care if symptoms are rapidly worsening or include a new neurological deficit or other warning sign.