

Trigeminal Neuralgia vs Dental Pain: How Can You Tell the Difference?
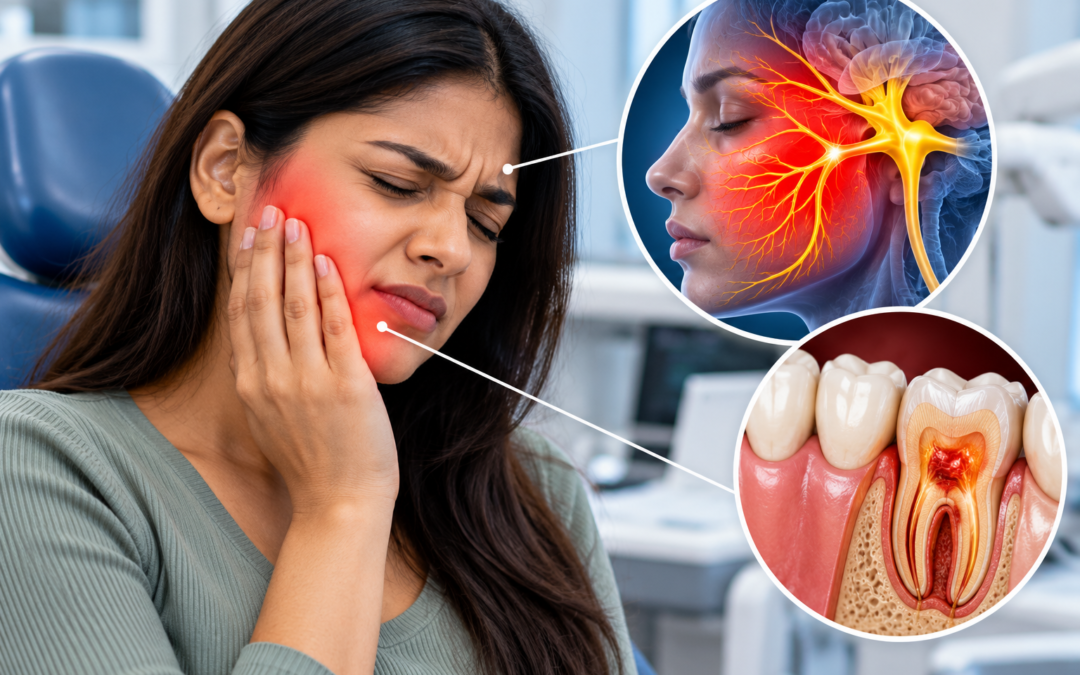
Trigeminal neuralgia vs dental pain is best approached as a diagnosis-and-function problem, not as a keyword or scan finding. Trigeminal neuralgia causes sudden, severe, electric-shock-like facial pain along one or more branches of the trigeminal nerve. Because attacks can be triggered by chewing, brushing teeth, washing the face, or cold air, patients may initially believe a tooth is the cause. Distinguishing trigeminal neuralgia vs dental pain is important because unnecessary dental procedures will not treat a nerve disorder, while genuine dental infection needs prompt dental care. This guide explains what patients should know, what a clinician may assess, where non-surgical care fits, and which warning signs should change the plan. The aim is to help readers ask better questions and understand the pathway from symptoms to an evidence-informed treatment decision. For readers who want condition-specific evaluation and treatment information, explore trigeminal neuralgia treatment at Epione.
Understanding the Problem Before Choosing Treatment
Patients often reach this topic after searching for related phrases such as trigeminal neuralgia tooth pain, facial nerve pain vs toothache, or electric shock pain in face. Those terms can describe overlapping problems, but they are not interchangeable diagnoses. A useful clinical approach separates the structure seen on imaging from the symptoms a person actually experiences. Two people can have similar scans and very different pain, strength, mobility, sleep, and daily function. This is why a clinician should connect the history, examination, and any tests before recommending treatment.
Symptoms, Causes and Why Similar Scans Can Feel Different
Pain is influenced by more than structural change alone. Tissue irritation, nerve sensitivity, inflammation, muscle guarding, sleep, stress, previous episodes, physical conditioning, and the demands placed on the body can all affect how strongly symptoms are felt. For this reason, related searches such as trigeminal neuralgia tooth pain or facial pain while chewing should lead to a proper assessment rather than self-diagnosis. A scan can be clinically useful, but it cannot measure pain intensity, explain every symptom, or determine by itself whether a person needs a procedure or surgery.
How a Clinician Builds the Diagnosis
The pain history is highly informative. Trigeminal neuralgia classically causes brief, recurrent, intense shocks with pain-free intervals, although some patients also have a continuous background ache. Dental pain is more often localized to a tooth, may be provoked by biting or temperature, and can be associated with swelling, tenderness, decay, or gum disease. A dental examination may be needed to exclude local causes. Neurological examination and MRI can be considered when trigeminal neuralgia is suspected, particularly with atypical features. A well-structured consultation also asks what the patient wants to regain: walking, sleeping, driving, working, exercising, or caring for family. These functional goals matter because a treatment that changes a scan report but does not improve daily life has limited practical value. Where appropriate, blood tests, electrodiagnostic studies, or specialist referrals may be used to rule out competing diagnoses.
If symptoms overlap with related pain patterns, the clinician may also consider facial nerve pain as part of the differential diagnosis and treatment pathway.
Non-Surgical Treatment Pathway
Treatment for confirmed trigeminal neuralgia commonly begins with medicines that reduce abnormal nerve firing. If medication is ineffective, poorly tolerated, or the diagnosis is complex, specialist options can include nerve procedures or neurosurgical treatments depending on the case. Interventional pain procedures may have a role in selected patients, but the choice depends on the affected branch, prior response, age, imaging, and comorbidities. Dental treatment should only be performed when a dental cause is established. In most non-emergency pain conditions, the first objective is to preserve safe movement and progressively rebuild capacity. Treatment should be stepped rather than random: establish the likely diagnosis, set measurable goals, start the least invasive reasonable option, reassess, and escalate only when the expected benefit justifies the risk. That principle is especially important for searches around trigeminal neuralgia symptoms, where a procedure may sound like a complete solution even though the best results often come from combining targeted pain relief with rehabilitation.
For patients whose symptoms fit the relevant indication, Epione also provides information about nerve block injections. The procedure should only be considered after diagnosis and suitability are established.
Where Interventional Pain Procedures May Fit
Interventional pain procedures can be useful when there is a specific clinical target, but they should not be used simply because pain has lasted a long time. The clinician should be able to explain what structure or nerve is being targeted, what diagnostic evidence supports it, what level of relief would count as success, and what the next step will be if the procedure does not help. Temporary pain reduction can still be valuable when it creates a window for walking, strengthening, sleep, work, or physiotherapy. It should not be confused with structural healing unless the treatment actually addresses the structure itself.
A related option that may be relevant for selected diagnoses is facial pain treatment; however, the indication, risks and expected benefit should be confirmed during consultation.
Rehabilitation and Long-Term Function
Rehabilitation is not one generic exercise sheet. The appropriate program depends on irritability, strength, balance, mobility, neurological findings, and the activities that matter to the patient. During a flare, the program may emphasize symptom control and tolerable movement. As symptoms settle, the focus can shift toward progressive loading, endurance, confidence, and return to normal activity. For chronic pain, pacing and consistency are often more useful than repeated cycles of overactivity followed by complete rest. Sleep, weight, diabetes control, smoking, stress, and work ergonomics can also influence recovery and should be addressed when relevant.
Red Flags: When Routine Blog Advice Is Not Enough
Facial pain with new facial weakness, persistent numbness, double vision, hearing changes, fever, facial swelling, eye involvement, or other neurological deficits should be assessed promptly because these features are not typical of uncomplicated trigeminal neuralgia. These warning signs are not included to alarm readers; they help distinguish routine outpatient pain care from situations that need urgent investigation. A new or rapidly changing symptom deserves more attention than a stable symptom that has already been evaluated.
How to Make a Better Treatment Decision
When considering trigeminal neuralgia vs dental pain, ask four practical questions: What is the most likely pain generator? What evidence supports that diagnosis? What is the least invasive reasonable treatment that could improve function? What would make the clinician change course? A high-quality plan also explains expected timelines, common side effects, follow-up, and what to do if symptoms worsen. For location-specific searches, convenience matters, but clinical reasoning, image guidance when required, sterile technique, follow-up, and transparent discussion of alternatives matter more than promotional claims.
Practical Tips Before Your Consultation
Practical steps that can make the consultation and treatment plan more useful include:
- Write down attack duration and exact triggers.
- Note whether pain is electric and brief or throbbing and persistent.
- Have a dental examination when tooth disease is a realistic possibility.
- Avoid repeated irreversible dental work without a confirmed dental diagnosis.
- Report numbness or neurological changes to the treating clinician.
Related Questions This Guide Helps Answer
This article is designed to answer the main topic naturally while also covering related patient questions around trigeminal neuralgia tooth pain, facial nerve pain vs toothache, electric shock pain in face, trigeminal neuralgia symptoms, and facial pain while chewing. These terms should be used contextually on-page rather than repeated mechanically.
Conclusion
The strongest approach to trigeminal neuralgia vs dental pain is individualized, diagnosis-led, and function-focused. Most patients benefit from understanding the cause of symptoms, using conservative care appropriately, and reserving procedures for situations where there is a clear target and a realistic goal. Persistent pain does not automatically mean surgery is required, and non-surgical care does not mean delaying necessary surgery when neurological or emergency findings are present. A qualified clinician can help match the level of treatment to the severity of symptoms, examination findings, previous response, and personal goals.
Talk to a Pain Specialist
If pain is persistent, recurrent, or limiting daily function, a clinical assessment can help identify the likely source and the least invasive appropriate next step. Visit Epione Pain Management Center to review services and appointment options.
Frequently Asked Questions
How is trigeminal neuralgia pain different from toothache?
Trigeminal neuralgia often causes brief electric-shock attacks triggered by light touch, chewing, or brushing. Dental pain is more often localized and linked to tooth pathology, biting, or temperature.
Can trigeminal neuralgia feel like pain in one tooth?
Yes. Pain can be perceived in the jaw or teeth because trigeminal branches supply these areas.
Should I see a dentist first?
If dental disease is possible, dental assessment is appropriate. Persistent electric shock-like pain with normal dental findings should prompt neurological or pain evaluation.
Does trigeminal neuralgia show on an X-ray?
Dental X-rays do not diagnose trigeminal neuralgia. MRI may be used to investigate the trigeminal nerve and exclude other causes.
What triggers trigeminal neuralgia?
Common triggers include chewing, talking, brushing teeth, washing the face, shaving, light touch, and cold air.
How is trigeminal neuralgia treated?
Medication is often first-line. Specialist procedures or surgery may be considered when symptoms remain severe or medicines are unsuitable.
Can dental extraction cure trigeminal neuralgia?
No, not when the pain is caused by trigeminal neuralgia rather than dental disease.
What symptoms are atypical?
Persistent numbness, weakness, bilateral pain, hearing or vision changes, or other neurological deficits require broader evaluation.